
GSK1324726A_1300031-52-0_DataSheet_MedChemExpress
进口药品注册标准目录2
甘氨酸 固体脂肪36型 固体脂肪38型 共聚维酮 H 黄凡士林 滑石粉
糊精
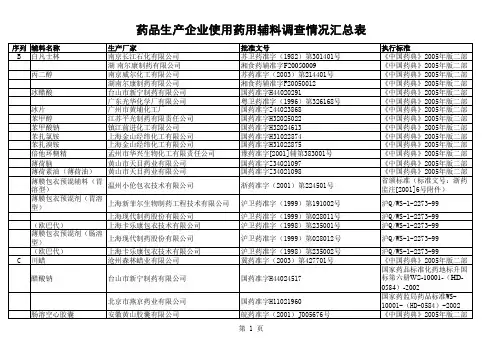
药品生产企业使用药用辅料调查情况汇总表
镇江市环宇药用辅料厂 海盐六和淀粉化工有限公司 嘉兴市白浪淀粉制品有限公司 华北制药康欣有限公司 安徽山河药用辅料有限公司 河南精忠威尔药业有限公司 J 甲基丙烯酸-丙烯酸乙酯 Rohm GmbH & Co.KG (德国进口) 共聚物水分散体 甲基丙烯酸共聚物A型 Rohm GmbH & Co.KG (德国进口) 聚维酮K30 湖州展望药业有限公司 BASF Corporation (美国进口) 安徽山河药用辅料有限公司 博爱新开源制药有限公司 海南南杭药业有限公司 聚山梨酯80(吐温80) 南京威尔化工有限公司 上海申宇医药化工有限公司 龙游聚兴粮油医药化工有限公司 北京市海淀会友精细化工厂 南京威尔化工有限公司 辽阳奥克纳米材料有限公司 北京海淀会友精细化工厂 上海浦东高南化工厂 南京威尔化工有限公司 International Specialty Products Inc. ( 美 国进口) 连云港华瑞化工有限责任公司 INTERNATIONAL SPECIALTY PRODUCTS INC.(美国进口) 苏卫药准字(94)第3022-2号 浙卫药准字(1998)第220902号 浙卫药准字(1996)第220901号 冀卫药准字(1995)第000057号 皖药准字(2002)第F0001号 豫药准字F20040002号 进口药品注册证号:H20060013 进口药品注册证号:H20060593 浙药准字F20060062号 进口药品注册证号:H20040430 皖药准字F20060001 (95)卫药准字F-01号 琼药准字F20040001 苏卫药准字(2001)第423201号 沪卫药准字(1995)第186001号 浙卫药准字(1996)第184101号 京卫药准字(95)第023号 苏卫药准字(2001)第423301号 辽药准字F(2004)第900033号 京卫药准字(95)第008号 沪卫药准字(1995)第105004号 苏卫药准字(2001)第423601号 进口药品注册证号:H20030492 苏卫药准字(1983)第308001号 进口药品注册证号:H20030278 第 3 页 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 进口药用辅料注册标准 JX20020020 进口药品注册标准 JX20020322 《中国药典》2005年版二部 进口药品注册标准 JX20030277 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 《中国药典》2005年版二部 进口药品注册标准 JX20020325 《中国药典》2005年版二部 进口药品注册标准 JX19990242
MG-132_DataSheet_MedChemExpress

Inhibitors, Agonists, Screening Libraries Data SheetBIOLOGICAL ACTIVITY:MG–132 is a potent, non–specific 20S proteasome inhibitor, with IC 50 of 24.2 nM for the β5 chymotrypsin –like active site.IC50 & Target: IC50: 24.2 nM (chymotrypsin–like activity)[1]In Vitro: Dose–dependent inhibition of cell growth is observed in HeLa cells with an IC 50 of approximately 5 μM MG132 for 24 h.MG132 inhibits the growth of HeLa cells via inducing the cell cycle arrest as well as triggering apoptosis [2]. MG–132 inhibits C6glioma cell proliferation in a time– and dose–dependent manner (the IC 50 value at 24 h is 18.5 μM). MG–132 (18.5 μM) suppresses the proteasome activity by about 70% at 3 h. MG–132 induces apoptosis via down–regulation of antiapoptotic proteins Bcl–2 and XIAP, up–regulation of pro–apoptotic protein Bax and caspase–3, and production of cleaved C–terminal 85 kDa PARP. MG–132 also causes a more than 5–fold increase of reactive oxygen species [3]. The IC 50 of MG–132 against HeLa, CaSki, and C33A cervical cancer cells viability after 48 h of incubation is 2.1, 3.2, and 5.2 μM, respectively [4].In Vivo: The in vivo antitumor activity of MG–132 against cervical cancer is examined using s.c. xenograft models. MG–132 is injected at 1 mg/kg using the following schedule: days 1, 4, 8, 12, 15 18, 23, and 26 for mice bearing HeLa tumors. The growth inhibition rates of MG132 compared to control is 49%[4]. MG–132 (i.p., 0.1 mg/kg/day) attenuates pressure–overload–induced cardiac hypertrophy and improves cardiac function in abdominal aortic banding (AAB) rats through regulation of ERK1/2 and JNK1signaling pathways [5].PROTOCOL (Extracted from published papers and Only for reference)Kinase Assay:[3]After growing on six–well plates (3×10⁵ cells/well) for 24 h, C6 glioma cells are treated with either PBS (control) or 18.5 μM MG–132 for 3, 6, 12, or 24 h at 37°C. Cells are thoroughly scraped from the culture dishes with a cell scraper and washed with cold PBS. After centrifugation for 10 min at 800×g, the cell pellets are suspended in ice–cold buffer (50 mM Tris–HCl, pH 7.5, 20μM ATP, 5 mM MgCl 2, 1 mM dithiothreitol, and 20% glycerol) and homogenized with a Pyrex glass microhomogenizer (20 strokes).The homogenate is centrifuged at 15 000×g for 10 min at 4°C to obtain supernatant. Protein concentration is determined using protein assay kits. A total of 10 μL (1 μg/μL) of each freshly made supernatant is incubated in a 96–well plate at 37°C for 30 min with 10 μL of 300 μM of Succinyl–LLVY–AMC and 85 μL of assay buffer (20 mM Tris–HCl, pH 7.5, and 20% glycerol). Release of fluorescent AMC is measured with a spectrofluorometer at 440 nm with an excitation wavelength of 380 nm [3].Cell Assay: MG–132 is dissolved in PBS to a storage concentration of 50 μM [3]. [3]C6 glioma cells are seeded onto 96–well microplates (3×10⁴ cells/well) and cultured for 24 h. The cells are treated with PBS or MG–132 final concentrations of 10, 20, 30, and 40 μM,respectively. Cell viability is assessed using an MTT assay at 3, 6, 12, and 24 h after MG–132 treatment. The absorbance value at 570nm is read using an automatic multi–well spectrophotometer. C6 glioma cells (3×10⁵ cells/well) are allowed to grow on coverslips in 6–well culture plates for 24 h. The cells are then treated with either PBS (control) or 18.5 μM MG–132 at 37°C for 24 h. Cells growing on glass coverslips are fixed in methanol for 5 min at room temperature. The fixed cells are washed twice with PBS and then incubated with Hoechst 33342 for 5 min at room temperature and observed under a fluorescence microscope. Fragmented orProduct Name:MG–132Cat. No.:HY-13259CAS No.:133407-82-6Molecular Formula:C 26H 41N 3O 5Molecular Weight:475.62Target:Proteasome Pathway:Metabolic Enzyme/Protease Solubility:10 mM in DMSOcondensed nuclei are scored as apoptotic[3].Animal Administration: MG–132 is dissolved in vehicle (saline) (Mice)[4].MG–132 is dissolved in vehicle (0.1% DMSO) (Rat)[5].[4][5]Mice[4]C.B–17/lcr–scid/scidJcl mice are inoculated s.c. with HeLa, CaSki, or C33A (1×10⁷ cells). Tumors are allowed to grow for 1 week. Mice are killed and tumors are removed. Tumors are then cut into 2–mm diameter pieces and s.c. transplanted inC.B–17/lcr–scid/scidJcl mice (n=6 per group). One week after inoculation, mice are treated with i.v. injection of saline (control),MG–132 (1 mg/kg/dose) twice a week for 4 weeks. The volume (V) of tumors is measured before every injection, as estimated using equation V=a×b2/2 where a and b are major and minor axes of the tumor measured by a caliper, respectively.Rat[5]Male Sprague–Dawley rats (8 weeks old, 180–230 g) are used to establish pressure–overload model. All animals are separated into four groups (10 rats per group): (i) vehicle–treated sham group; (ii) MG–132–treated sham group; (iii) vehicle–treated abdominal aortic banding (AAB) group; and (iv) MG–132–treated AAB group. Under intraperitoneal pentobarbital (50 mg/kg) anesthesia, AAB is created using a 5–0 suture tied twice around the abdominal aorta in which a 21–gauge needle is inserted. The needle is then retracted yielding a 70–80% constriction with an outer aortic diameter of ~0.8 mm. In the sham surgery rats, the same surgery is performed except the aorta is constricted. At Day 3 after the surgery, MG–132–treated rats are intraperitoneally injected with 0.1 mg/kg/day of MG–132 for 8 weeks. All control animals are injected with a corresponding volume of vehicle only (0.1% DMSO).References:[1]. Braun HA, et al. Tripeptide mimetics inhibit the 20 S proteasome by covalent bonding to the active threonines. J Biol Chem. 2005 Aug 5;280(31):28394–401.[2]. Han YH, et al. The effect of MG132, a proteasome inhibitor on HeLa cells in relation to cell growth, reactive oxygen species and GSH. Oncol Rep. 2009 Jul; 22(1):215–21.[3]. Fan WH, et al. Proteasome inhibitor MG–132 induces C6 glioma cell apoptosis via oxidative stress. Acta Pharmacol Sin. 2011 May;32(5):619–25.[4]. Matsumoto Y, et al. Enhanced efficacy against cervical carcinomas through polymeric micelles physically incorporating theproteasome inhibitor MG132. Cancer Sci. 2016 Jun;107(6):773–81.[5]. Chen B, et al. MG132, a proteasome inhibitor, attenuates pressure–overload–induced cardiac hypertrophy in rats by modulation of mitogen–activated protein kinase signals. Acta Biochim Biophys Sin (Shanghai). 2010 Apr;42(4):253–8.Caution: Product has not been fully validated for medical applications. For research use only.Tel: 609-228-6898 Fax: 609-228-5909 E-mail: tech@Address: 1 Deer Park Dr, Suite Q, Monmouth Junction, NJ 08852, USA。
UPLC-DAD波长切换法同时测定复方红衣补血口服液中6种多酚类化合物的含量

中图分类号:R 921 2 文献标识码:A 文章编号:1009 - 3656(2021)03 - 0283 - 06
doi:10 19778 / j chp 2021 03 018
Simultaneous determination of six polyphenols in Compound Hongyi
30、43 ng mL - 1 ꎻ 精 密 度、 稳 定 性、 重 复 性 试 验 的 RSD 均 小 于 2 0% ꎻ 平 均 加 样 回 收 率 分 别 为 98 56%
( RSD = 2 26% ꎬn = 9 ) 、 97 94% ( RSD = 1 54% ꎬ n = 9 ) 、 97 23 % ( RSD = 2 19% ꎬ n = 9 ) 、 98 54%
摘要 目的: 建立超高效液相色谱 ̄DAD 波长切换法同时测定复方红衣补血口服液中咖啡酸、没食子酸、对
羟基肉桂酸、阿魏酸、儿茶素、表儿茶素含量的方法ꎮ 方法:采用高效液相色谱法ꎮ 色谱柱为 Waters Symme ̄
try C18 (4 6 mm × 150 mmꎬ3 5 μm) ꎬ流动相为甲醇 ̄0 1% 甲酸溶液( 梯度洗脱) ꎬ流速为 0 5 mLmin - 1 ꎬ检测
2 方法与结果
2 1 色谱条件与系统适用性
色谱 柱: Waters Symmetry C18 ( 4 6 mm × 150
的质量研究是以儿茶素 [10] 、白藜芦醇 [11] 单一成分
mmꎬ3 5 μm) ꎻ 流 动 相: 甲 醇 ( A)  ̄0 1% 甲 酸 溶 液
定ꎮ 本研究建立 UPLC 法同时测定复方红衣补血口
美国贝克曼库尔特流式细胞分析仪

美国贝克曼库尔特流式细胞分析仪(Beckman coulter cell)产品型号:Cell Lab Quanta SC当前价格:0.00元产品数量:0新旧程度:全新有效期至:0000-00-00所在地:产品简介:仪器简介:T细胞亚群检测的CD45/CD4/CD8/CD3、CD45/CD56/CD19/CD3;阵发性血红蛋白尿(PNH)检测的CD55、CD59;血小板无力症(GT)检测的CD41、CD61等等详细信息仪器简介:T细胞亚群检测的CD45/CD4/CD8/CD3、CD45/CD56/CD19/CD3;阵发性血红蛋白尿(PNH)检测的CD55、CD59;血小板无力症(GT)检测的CD41、CD61等等。
但对于白血病/淋巴瘤免疫分型,国际上迄今为止也没有统一的抗体组合。
在2000年国际细胞分析学会(ISAC)大会上,临床血细胞计数协会组织了一次国际专家会议,以期对检测血液淋巴系统肿瘤所需最少、最有效的单抗数达成共识。
75%与会者一致认为,对于慢性淋巴系统增殖性疾病(CLD)有9种单抗:CD5,CD19,κ,λ,CD3,CD20,CD23,CD10,CD45对初诊来说是最基本的。
淋巴瘤和CLD相似,需要至少12-16种单抗。
对于急性白血病(AL),75%的与会者认为大约13-15种单抗是最基本的:CD10,CD19,CD79a,CD13,CD33,CD34,CD45,CD2,MPO,CD7,CD14,CD3,HLA-DR等,对初步鉴别白血病系列是必需的。
其他一些(CD16,CD56,CDw65,TdT,cyCD3)可能对某些病例有用。
几乎所有的投票者都认为,要对急性白血病完善分类所需单抗的恰当数量平均为20-24种。
但这些抗体之间组合也是一大难题,目前也无统一规定(如表二)。
大会多数发言者(11/13)指出,对已确诊病人的监护和分期来说,仅需较少单抗。
抗体的质量控制是实验的关键环节。
抗体的质量包括其特异性、灵敏度、精密度。
GSK1324726A_SDS_MedChemExpress

Inhibitors, Agonists, Screening LibrariesSafety Data Sheet Revision Date:May-24-2017Print Date:May-24-20171. PRODUCT AND COMPANY IDENTIFICATION1.1 Product identifierProduct name :GSK1324726ACatalog No. :HY-13960CAS No. :1300031-52-01.2 Relevant identified uses of the substance or mixture and uses advised againstIdentified uses :Laboratory chemicals, manufacture of substances.1.3 Details of the supplier of the safety data sheetCompany:MedChemExpress USATel:609-228-6898Fax:609-228-5909E-mail:sales@1.4 Emergency telephone numberEmergency Phone #:609-228-68982. HAZARDS IDENTIFICATION2.1 Classification of the substance or mixtureGHS Classification in accordance with 29 CFR 1910 (OSHA HCS)Acute toxicity, Oral (Category 4),H302Acute aquatic toxicity (Category 1),H400Chronic aquatic toxicity (Category 1),H4102.2 GHS Label elements, including precautionary statementsPictogramSignal word WarningHazard statement(s)H302 Harmful if swallowed.H410 Very toxic to aquatic life with long lasting effects.Precautionary statement(s)P264 Wash skin thoroughly after handling.P270 Do not eat, drink or smoke when using this product.P273 Avoid release to the environment.P301 + P312 IF SWALLOWED: Call a POISON CENTER or doctor/ physician if you feel unwell.P330 Rinse mouth.P391 Collect spillage.P501 Dispose of contents/ container to an approved waste disposal plant.2.3 Other hazardsNone.3. COMPOSITION/INFORMATION ON INGREDIENTS3.1 SubstancesSynonyms:I⁻BET726; GSK 1324726A; GSK⁻1324726A; I⁻BET 726Formula:C25H23ClN2O3Molecular Weight:434.91CAS No. :1300031-52-04. FIRST AID MEASURES4.1 Description of first aid measuresEye contactRemove any contact lenses, locate eye-wash station, and flush eyes immediately with large amounts of water. Separate eyelids with fingers to ensure adequate flushing. Promptly call a physician.Skin contactRinse skin thoroughly with large amounts of water. Remove contaminated clothing and shoes and call a physician.InhalationImmediately relocate self or casualty to fresh air. If breathing is difficult, give cardiopulmonary resuscitation (CPR). Avoid mouth-to-mouth resuscitation.IngestionWash out mouth with water; Do NOT induce vomiting; call a physician.4.2 Most important symptoms and effects, both acute and delayedThe most important known symptoms and effects are described in the labelling (see section 2.2).4.3 Indication of any immediate medical attention and special treatment neededTreat symptomatically.5. FIRE FIGHTING MEASURES5.1 Extinguishing mediaSuitable extinguishing mediaUse water spray, dry chemical, foam, and carbon dioxide fire extinguisher.5.2 Special hazards arising from the substance or mixtureDuring combustion, may emit irritant fumes.5.3 Advice for firefightersWear self-contained breathing apparatus and protective clothing.6. ACCIDENTAL RELEASE MEASURES6.1 Personal precautions, protective equipment and emergency proceduresUse full personal protective equipment. Avoid breathing vapors, mist, dust or gas. Ensure adequate ventilation. Evacuate personnel to safe areas.Refer to protective measures listed in sections 8.6.2 Environmental precautionsTry to prevent further leakage or spillage. Keep the product away from drains or water courses.6.3 Methods and materials for containment and cleaning upAbsorb solutions with finely-powdered liquid-binding material (diatomite, universal binders); Decontaminate surfaces and equipment by scrubbing with alcohol; Dispose of contaminated material according to Section 13.7. HANDLING AND STORAGE7.1 Precautions for safe handlingAvoid inhalation, contact with eyes and skin. Avoid dust and aerosol formation. Use only in areas with appropriate exhaust ventilation.7.2 Conditions for safe storage, including any incompatibilitiesKeep container tightly sealed in cool, well-ventilated area. Keep away from direct sunlight and sources of ignition.Recommended storage temperature:Powder-20°C 3 years4°C 2 yearsIn solvent-80°C 6 months-20°C 1 monthShipping at room temperature if less than 2 weeks.7.3 Specific end use(s)No data available.8. EXPOSURE CONTROLS/PERSONAL PROTECTION8.1 Control parametersComponents with workplace control parametersThis product contains no substances with occupational exposure limit values.8.2 Exposure controlsEngineering controlsEnsure adequate ventilation. Provide accessible safety shower and eye wash station.Personal protective equipmentEye protection Safety goggles with side-shields.Hand protection Protective gloves.Skin and body protection Impervious clothing.Respiratory protection Suitable respirator.Environmental exposure controls Keep the product away from drains, water courses or the soil. Cleanspillages in a safe way as soon as possible.9. PHYSICAL AND CHEMICAL PROPERTIES9.1 Information on basic physical and chemical propertiesAppearance Light yellow to yellow (Solid)Odor No data availableOdor threshold No data availablepH No data availableMelting/freezing point No data availableBoiling point/range No data availableFlash point No data availableEvaporation rate No data availableFlammability (solid, gas)No data availableUpper/lower flammability or explosive limits No data availableVapor pressure No data availableVapor density No data availableRelative density No data availableWater Solubility No data availablePartition coefficient No data availableAuto-ignition temperature No data availableDecomposition temperature No data availableViscosity No data availableExplosive properties No data availableOxidizing properties No data available9.2 Other safety informationNo data available.10. STABILITY AND REACTIVITY10.1 ReactivityNo data available.10.2 Chemical stabilityStable under recommended storage conditions.10.3 Possibility of hazardous reactionsNo data available.10.4 Conditions to avoidNo data available.10.5 Incompatible materialsStrong acids/alkalis, strong oxidising/reducing agents.10.6 Hazardous decomposition productsUnder fire conditions, may decompose and emit toxic fumes.Other decomposition products - no data available.11.TOXICOLOGICAL INFORMATION11.1 Information on toxicological effectsAcute toxicityClassified based on available data. For more details, see section 2Skin corrosion/irritationClassified based on available data. For more details, see section 2Serious eye damage/irritationClassified based on available data. For more details, see section 2Respiratory or skin sensitizationClassified based on available data. For more details, see section 2Germ cell mutagenicityClassified based on available data. For more details, see section 2CarcinogenicityIARC: No component of this product present at a level equal to or greater than 0.1% is identified as probable, possible or confirmed human carcinogen by IARC.ACGIH: No component of this product present at a level equal to or greater than 0.1% is identified as a potential or confirmed carcinogen by ACGIH.NTP: No component of this product present at a level equal to or greater than 0.1% is identified as a anticipated or confirmed carcinogen by NTP.OSHA: No component of this product present at a level equal to or greater than 0.1% is identified as a potential or confirmed carcinogen by OSHA.Reproductive toxicityClassified based on available data. For more details, see section 2Specific target organ toxicity - single exposureClassified based on available data. For more details, see section 2Specific target organ toxicity - repeated exposureClassified based on available data. For more details, see section 2Aspiration hazardClassified based on available data. For more details, see section 212. ECOLOGICAL INFORMATION12.1 ToxicityNo data available.12.2 Persistence and degradabilityNo data available.12.3 Bioaccumlative potentialNo data available.12.4 Mobility in soilNo data available.12.5 Results of PBT and vPvB assessmentPBT/vPvB assessment unavailable as chemical safety assessment not required or not conducted.12.6 Other adverse effectsNo data available.13. DISPOSAL CONSIDERATIONS13.1 Waste treatment methodsProductDispose substance in accordance with prevailing country, federal, state and local regulations.Contaminated packagingConduct recycling or disposal in accordance with prevailing country, federal, state and local regulations.14. TRANSPORT INFORMATIONDOT (US)This substance is considered to be non-hazardous for transport.IMDGUN number: 3077Class: 9Packing group: IIIEMS-No: F-A, S-FProper shipping name: ENVIRONMENTALLY HAZARDOUS SUBSTANCE, SOLID, N.O.S.Marine pollutant: Marine pollutant.IATAUN number: 3077Class: 9Packing group: IIIProper shipping name: Environmentally hazardous substance, solid, n.o.s.15. REGULATORY INFORMATIONSARA 302 Components:No chemicals in this material are subject to the reporting requirements of SARA Title III, Section 302.SARA 313 Components:This material does not contain any chemical components with known CAS numbers that exceed the threshold (De Minimis) reporting levels established by SARA Title III, Section 313.SARA 311/312 Hazards:No SARA Hazards.Massachusetts Right To Know Components:No components are subject to the Massachusetts Right to Know Act.Pennsylvania Right To Know Components:No components are subject to the Pennsylvania Right to Know Act.New Jersey Right To Know Components:No components are subject to the New Jersey Right to Know Act.California Prop. 65 Components:This product does not contain any chemicals known to State of California to cause cancer, birth defects, or anyother reproductive harm.16. OTHER INFORMATIONCopyright 2017 MedChemExpress. The above information is correct to the best of our present knowledge but does not purport to be all inclusive and should be used only as a guide. The product is for research use only and for experienced personnel. It must only be handled by suitably qualified experienced scientists in appropriately equipped and authorized facilities. The burden of safe use of this material rests entirely with the user. MedChemExpress disclaims all liability for any damage resulting from handling or from contact with this product.Caution: Product has not been fully validated for medical applications. For research use only.Tel: 609-228-6898 Fax: 609-228-5909 E-mail: tech@Address: 1 Deer Park Dr, Suite Q, Monmouth Junction, NJ 08852, USA。
反相高效液相色谱法测定化妆品或洗涤用品中对氯二甲苯酚、三氯卡班和三氯生

#" 结果与讨论
# ! !" 实验条件的选择 , , 资料检索[ $ ]及实验表明, 以乙腈与水或甲醇与水按不同 比例混合作 流 动 相 时, 三氯卡班和三氯生不能达到基线分 离, 即使采用梯度法, 也无济于事[ ! ]。经试验, 本方法选择四 氢呋喃 + 水 ( 体积比为 %". #" ) 作流动相可同时测定对氯二甲 苯酚、 三氯卡班和三氯生, 三组分获得很好的分离。 # ! #" 线性关系与检出限 , , 按上述色谱条件 分 别 注 入 系 列 质 量 浓 度 的 混 合 标 准 溶 测定峰面积, 以氯二 甲 苯 酚、 三氯卡班和三氯生 液各 $" ! D , 的质量浓度 ! ( %G E D ) 对相应 的 峰 面 积 " 作 图, 三 者 均 在 $" / !"" %G E D 范围内与其各 自 对 应 的 峰 面 积 呈 线 性 关 系。 其 线性回归方程分别为 " # $( !"" ! H $+ &"" ( $ I "- ’’’ ’& ) , " # +" #"" ! J # ($" ( $ I "- ’’’ #! ) 和 " I !# &"" ! H (# #"" ($ I "- ’’’ ’) ) 。经实验测定,对氯二甲苯酚、 三氯卡班和三 氯 生的最低检测量 ( % & ’ I () 分 别 为 $, "- $ 和 $ 6G , 最低检测 分别为 "- $ , "- "$ 和 "- $ %G E D 。 质量浓度 ( % & ’ I () # ! $" 精密度及回收率试验 , , 将混合标准溶液在进样量为 "- & , $- & ! G 两 个 不 同 质 量 得 到 对 氯 二 甲 苯 酚、 三氯卡班和三氯生 水平下各进样 % 次, 峰面积的 相 对 标 差 偏 差 ( KAL ) 分 别 为 "- $" , "- $& , "- $) 及
GSK1324726A_I-BET726_BET蛋白抑制剂_CAS号1300031-52-0_M9146说明书_AbMole中国
分子量434.91溶解性(25°C)DMSO ≥ 43 mg/mL分子式C25H23ClN2O3Water InsolubleCAS号1300031-52-0Ethanol储存条件3年 -20°C 粉末状生物活性GSK1324726A(I-BET726)是一种有效的选择性BET蛋白抑制剂,对BRD2,BRD3和BRD4的IC50值分别为41 nM,31 nM和22 nM。
GSK1324726A在神经母细胞瘤细胞系中,有效抑制细胞生长并诱导细胞毒性。
体内研究中,在小鼠SK-N-AS和CHP-212模型中,GSK1324726A(15 mg/kg, p.o.)抑制肿瘤生长,并下调MYCN和BCL2的表达。
在小鼠感染性休克模型中,GSK1324726A (10 mg/kg, i.v.)表现出有效的抗炎作用。
实验操作来自于公开的文献,仅供参考细胞实验细胞系方法浓度处理时间动物实验动物模型Xenograft models of non-MYCN-amplified and MYCN-amplified neuroblastoma in immunocompromised mice using the SK–N-AS and CHP-212 cell lines配制Suspended in 1% methylcellulose剂量15 mg/kg once daily给药处理p.o.不同实验动物依据体表面积的等效剂量转换表(数据来源于FDA指南)小鼠大鼠兔豚鼠仓鼠狗重量 (kg)0.020.15 1.80.40.0810体表面积 (m)0.0070.0250.150.050.020.5K系数36128520动物 A (mg/kg) = 动物 B (mg/kg) ×动物 B的K系数动物 A的K系数例如,依据体表面积折算法,将白藜芦醇用于小鼠的剂量22.4 mg/kg 换算成大鼠的剂量,需要将22.4 mg/kg 乘以小鼠的K系数(3),再除以大鼠的K系数(6),得到白藜芦醇用于大鼠的等效剂量为11.2 mg/kg。
蛋白核酸样品制备-bio-rad产品介绍
Quantum Prep质粒中型制备试剂盒采用了简便的离心柱操作流程,显著地缩短了大量质粒DNA制备所需的时间,所制备的DNA可用于转染、亚克隆和其它酶处理。
Chelex树脂
Bio-Rad提供两种以Chelex为基质的树脂,用于从多种粗样品(如血液、细菌、组织和头发)中抽提DNA。由于所抽提的DNA通常用于下游的PCR,因此它必须不含能抑制扩增反应的金属离子,Chelex由成对的亚氨基二乙酸离子结合在苯乙烯二乙烯苯基质上形成,对多价阳离子具有很强的选择性,从而有效地去除这类污染杂质。
■■哺乳动物、植物、酵母、微生物样品的细胞裂解和蛋白抽提实验方法
■■该试剂盒能使用于任何特殊种类的蛋白提取,不仅局限于下游MicroRotofor等电聚焦
■■试剂盒抽提的蛋白样品结果,不必再改变缓冲液条件,而能迅速使用MicroRotofor进行等电聚焦实验。
ReadyPrep小研磨试剂盒
Readyprep mini grinders研磨处理小量生物样品,对于核酸和蛋白质具有极高的回收率,每个小研磨棒( minigrinders )包括1.5ml含研磨树脂的研磨管和相应的研磨杵,研磨树脂是一种中性强张力的微粒状研磨剂,不与蛋白质和核酸结合。Readyprep mini grinders是一次性使用的试剂盒,并且不含有核酸酶或蛋白酶,他们也是MicroRotofor裂解试剂盒(哺乳动物)的组成成分,可以分开单独出售,每20个为一个包装,mini grinders具有以下特性:
Aurum质粒小型制备试剂盒能为ቤተ መጻሕፍቲ ባይዱ下领域的研究制备高产量重现性高的质粒DNA:
■■全自动荧光测序
■■限制性酶切
■■连接和转化
■■转染
Invitrogen TrueCut Cas9 Proteins 说明书
For Research Use Only. Not for use in diagnostic procedures.TrueCut ™ Cas9 ProteinsCatalog Nos.A36496, A36497, A36498, A36499, A50574, A50575, A50576, A50577WARNING! Read the Safety Data Sheets (SDSs) and follow the handling instructions. Wear appropriate protective eyewear, clothing, and gloves. Safety Data Sheets (SDSs) are available from thermofi/support .Product descriptionInvitrogen ™ TrueCut ™ Cas9 Proteins are used for genome editing applications with CRISPR technology. Cas9 protein forms a very stable ribonucleoprotein (RNP) complex with the guide RNA (gRNA) component of the CRISPR-Cas9 system. Incorporation of nuclear localization signals (NLS) aid its delivery to the nucleus, increasing the rate of genomic DNA cleavage. It is cleared rapidly, minimizing the chance for off-target cleavage when compared to plasmid systems (Liang et al ., 2015). The Cas9 nuclease hasbeen tested in a wide variety of suspension and adherent cell lines and has shown superior genomic cleavage efficiencies and cell survivability compared to plasmid-based CRISPR systems.Two types of TrueCut ™ Cas9 Proteins are available for selection, depending upon the requirements of your particular experiment:• TrueCut ™ Cas9 Protein v2 is a recombinant Streptococcus pyogenes Cas9 (wt) protein that is the preferred choice for most CRISPR genome editing procedures where the highest level of editing efficiency is required. • TrueCut ™ HiFi Cas9 Protein is an engineered high fidelity Cas9 protein which is ideal for experiments that are sensitive to off-target events, while still maintaining a high level of editing efficiency.Table 1.Contents and storagePub. No. MAN0017066Rev.D.0Storage and handling• Store TrueCut ™ Cas9 Protein v2 and TrueCut ™ HiFi Cas9 Protein at –20°C until required for use. • Maintain RNAse-free conditions by using RNAse-free reagents, tubes, and barrier pipette tips while setting up your experiments.Before you beginMaterials required but notprovided• TrueGuide™ Synthetic gRNAs (see /trueguide)orGeneArt™ Precision gRNA Synthesis Kit (Cat. No. A29377)• Lipofectamine™ CRISPRMAX™ Cas9 Transfection Kit (Cat. Nos. CMAX00001,CMAX00003, CMAX00008, CMAX00015, CMAX00030) (for most cell lines)orNeon™ Transfection System (Cat. Nos. MPK5000, MPK1025, MPK1096) (for highesttransfection efficiency in challenging cell types including suspension cell lines)• GeneArt™ Genomic Cleavage Detection Kit (Cat. No. A24372)• Opti-MEM™ I Reduced Serum Medium (Cat. No. 31985-062)• 1X TE buffer, pH 8.0 (Cat. No. AM9849) and nuclease-free water (Cat. No. AM9914G)Prepare working stock ofTrueGuide™ Synthetic gRNA If TrueGuide™ Synthetic gRNA is being used, resuspend the gRNA (sgRNA, crRNA, ortracrRNA) in1X TE buffer to prepare 100 μM (100 pmol/μL) stock solutions.Before opening, centrifuge each TrueGuide™ Synthetic gRNA tube at low speed (maximum1.RCF 4,000 × g) to collect the contents at the bottom of the tube, then remove the cap from thetube carefully.Using a pipette and sterile tips, add the required volume of 1X TE buffer to prepare 100 μM2.(100 pmol/μL) stock solutions.3.Vortex the tube to resuspend the oligos, briefly centrifuge to collect the contents at thebottom of the tube, then incubate at room temperature for 15–30 minutes to allow the gRNAoligos to dissolve.Vortex the tube again to ensure that all the contents of the tube are resuspended, then briefly4.centrifuge to collect the contents at the bottom of the tube.(Optional) Check the concentration of the resuspended oligos using the NanoDrop™5.Spectrophotometer (or equivalent) or a UV-base plate reader.6.(Optional) Aliquot the working stock into one or more tubes for storage.Use working stocks immediately or freeze at –20°C until needed for use.7.(Optional) Generate gRNA byin vitro transcription If using in vitro transcribed gRNA with TrueCut™ Cas9 Protein v2 or TrueCut™ HiFi Cas9Protein in CRISPR-Cas9-mediated genome editing, the GeneArt™ Precision gRNA SynthesisKit is recommended for preparation of the gRNA. For detailed instructions on how togenerate full length gRNA, see the GeneArt™ Precision gRNA Synthesis Kit User Guide (Pub.No. MAN0014538), at .Transfection guidelinesGeneral CRISPR/gRNAtransfection guidelines• The efficiency with which mammalian cells are transfected with gRNA varies accordingto cell type and the transfection reagent used. See Table 2 (page 3) for delivery reagentrecommendations.• For gene editing (including gene knockout) editing efficiency is highest with a 1:1 molarratio of gRNA to TrueCut™ Cas9 Protein v2 or TrueCut™ HiFi Cas9 Protein. In some celltypes such as iPSC and THP1, we have used up to 2 μg TrueCut™ Cas9 Protein v2 and400 ng gRNA per well in 24-well format.• For HDR knock-in editing, a 1.5:1 molar ratio of donor ssODN to gRNA or TrueCut™ Cas9Protein v2 or TrueCut™ HiFi Cas9 Protein is recommend for highest knock-in efficiency.The donor can be added directly to RNPs (a premixed gRNA-Cas9 protein). If using adsDNA donor, further optimization may be necessary to determine the appropriate donoramount, since the toxicity level is dependent on the length and format of the donor DNAand cell type.• The optimal cell density for transfection varies depending on cell size and growthcharacteristics. In general, use cells at 30–70% confluence on the day of transfectionwith lipid-mediated delivery, or 70–90% confluence for electroporation using the Neon™Transfection System.• After the optimal cell number and dosage of Cas9/gRNA and/or donor that providesmaximal gene editing efficiency is determined for a given cell type, do not varyconditions across experiments to ensure consistency.For an overview of the factors that influence transfection efficiency, see the “TransfectionBasics” chapter of the Gibco™ Cell Culture Basic Handbook, available at /cellculturebasics.• Use the TrueGuide™ Positive Controls (human AVVS1, CDK4, HPRT1, or mouse Rosa 26)and negative control gRNA (non-coding) to determine gRNA amount and transfectionconditions that give the optimal gene editing efficiency with highest cell viability. TheTrueGuide™ Positive and Negative sgRNA and crRNA Controls are available separatelyfrom Thermo Fisher Scientific. For more information, refer to /trueguide.• The cell number and other recommendations provided in the following proceduresare starting point guidelines based on the cell types we have tested. For multiplewells, prepare a master mix of components to minimize pipetting error, then dispense theappropriate volumes into each reaction well. When making a master mix for replicate wells,we recommend preparing extra volume to account for any pipetting variations.Recommended deliveryoptions• Choosing the right delivery reagent is critical for transfection and gene editing efficiency.See our recommendations in Table 2. For more information on transfection reagents, see/transfection.• For cell line specific transfection conditions using the Lipofectamine™ CRISPRMAX™Transfection Reagent or the Neon™ Transfection System, see the Appendix (page 13).• For best results, perform electroporation and transfection of cells using both TrueCut™Cas9 Proteins and TrueGuide™ Synthetic gRNA.HiFi Cas9 Protein.Table 2. Recommended delivery options for TrueCut™ Cas9 Protein v2 and TrueCut™Guidelines for verification of editing efficiencyVerification of gene editingefficiency• Before proceeding with downstream applications, verify the gene editing efficiency of thecontrol target and select the condition that shows the highest level of editing efficiency forfuture screening experiments.• To estimate the CRISPR-Cas9-mediated editing efficiency in a pooled cell population,use the GeneArt™ Genomic Cleavage Detection Kit (Cat. No. A24372), or performIon Torrent™ next generation sequencing or a Sanger sequencing-based analysis.• While the genomic cleavage detection (GCD) assay provides a rapid method forevaluating the efficiency of indel formation following an editing experiment, nextgeneration sequencing (NGS) of the amplicons from the edited population or Sangersequencing of amplicons cloned into plasmids give a more accurate estimate of thepercent editing efficiency and indel types for knockout and HDR knock-in editing.GeneArt™ Genomic CleavageDetection (GCD) Assay• After transfections, use the GeneArt™ Genomic Cleavage Detection Kit (Cat. No. A24372)to estimate the CRISPR-Cas9-mediated cleavage efficiency in a pooled cell population.• You can design and order target-specific primer sets for the GCD assay through ourTrueDesign Genome Editor, available at /crisprdesign.• To perform the GCD assay for the positive control, you need the primers listed in Table 3.We recommend using Invitrogen™ Custom DNA Value or Standard Oligos, available from/oligos, for target specific primer sets needed for the GCD assay.• You can set up the GCD assay in a 96-well plate format and analyze multiple gRNA-treated samples in parallel on a 2% E-Gel™ 48 agarose gel (48-well).• For more information and detailed protocols, see the GeneArt™ Genomic Cleavage DetectionKit User Guide (Pub. No. MAN0009849), available for download at /GCDManual.Table 3. Target sequences for the positive and negative control (non-targeting) TrueGuide™ Synthetic gRNA sequences.Guidelines for clone isolation and validationAfter you have determined the cleavage efficiency of the pooled cell population, isolate single cell clones for further validation and banking. You can isolate single cell clones from the selected pool using limiting dilution cloning (LDC) in 96-well plates or by single cell sorting using a flow cytometer.Limiting dilution cloning(LDC)• Based on the editing efficiency and estimated cell viability, you can estimate the number of single clones needed to obtain a desired knock-out (KO) clonal cell line. For example, if you desire a homozygous KO with mutations in both copies of a gene and the resulting GeneArt ™ cleavage detection efficiency was 50%, then the probability of having both alleles knocked out in any cell is 25% (0.5 × 0.5 = 0.25).If the probability of an indel leading to frame shift is 2/3, then the chance of having a homozygous KO is ~11% per cell [(0.5 × 0.5) × (0.66 × 0.66) = 0.11].• We recommend performing limiting dilution by targeting 0.8 cells/well, which requires you to resuspend the transfected cells (post-counting) at a density of8 cells/mL in complete growth medium, then transferring 100 µL of this to each well of a 96-well plate. If you plate at least ten 96-well plates in this manner and expect only 20% of cells tosurvive, then the probability of having homozygous KO clones in the 192 surviving cells will be 19–21 cells (192 × 11%).• Note that single cell clone survivability varies by cell type. Some cells that do not like to remain as single cells need to be plated at a low density to get well separated colonies, which will then have to be manually picked for further screening.Example LDC procedureusing 293FT cells1. Wash the transfected cells in each well of the 24-well plate with 500 µL of PBS. Carefully aspirate the PBS and discard.2. Add 500 µL of TrypLE ™ cell dissociation reagent to the cells and incubate for2–5 minutes at 37°C.3. Add 500 µL of complete growth medium to the cells to neutralize the dissociation reagent.Pipette the cells up and down several times to break up the cell aggregates. Make sure that the cells are well separated and are not clumped together. 4. Centrifuge the cells at 300 × g for 5 minutes to pellet.5. Aspirate the supernatant, resuspend the cells in an appropriate volume of pre-warmed(37°C) growth medium, then perform a cell count. 6. Dilute the cells to a density of 8 cells/mL of complete growth medium. Prepare a total ofSequence analysis• For next generation sequencing (NGS) based editing efficiency analysis, you canspecifically amplify the edited region and barcode amplicons by pooling all amplicons in a single tube and performing sequencing using various NGS platforms such as the Ion Torrent ™ Targeted Amplicon-seq Validation (TAV). For more information on NGS analysis, refer to Ion Torrent ™ targeted sequencing solutions at /ionapliseqsolutions .• For Sanger sequencing-based editing efficiency analysis, refer to our application note referenced at /sangercrispr .• Use the SeqScreener Gene Edit Confirmation App on Thermo Fisher ™ Connect todetermine the spectrum and frequency of targeted mutations (see Pub. No. MAN0019454 at . for details).50 mL of cell suspension at this cell density and transfer to a sterile reservoir.Note: You can also perform a serial dilution to get a better estimate of cell density.Using a multichannel pipettor, transfer 100 µL of the cell suspension into each well of 96-well7.tissue culture plates until the desired number of plates is seeded. Make sure to mix the cellsin between seeding the plates to avoid the formation of cell aggregates.Note: In general, we seed ten 96-well plates to achieve a large number of clones. Numberof plates to seed depends on the editing efficiency of pooled cell population and viability ofcells post single cell isolation.Incubate the plates in a 37°C, 5% CO2 incubator.8.Scan the plates for single cell colonies as soon as small aggregates of cells are visible under a9.4X microscope (usually after first week, depending on the growth rate of the cell line).Continue incubating the plates for an additional 2–3 weeks to expand the clonal populations10.for further analysis and characterization.Example single cell sortingprocedure in a 96-well plateusing flow cytometer Single cells can be sorted into a 96-well plate format using a flow cytometer with singlecell sorting capability. After sorting and expanding the single cell clones, analyze andcharacterize the clonal populations using suitable assays.1.Wash the transfected 293FT cells in each well of the 24-well plate with 500 µL of PBS.Carefully aspirate the PBS and discard.Add 500 µL of TrypLE™ cell dissociation reagent and incubate for 2–5 minutes at 37°C.2.Add 500 µL of complete growth medium to the cells to neutralize the dissociation reagent.3.Pipette the cells up and down several times to break up the cell aggregates. Make sure thatthe cells are well separated and are not clumped together.Centrifuge the cells at 300 × g for 5 minutes to pellet.4.5.Aspirate the supernatant, then wash the cell pellet once with 500 μL of PBS.Resuspend 1 × 10⁶ cells in 1 mL of FACS buffer, then add propidium iodide (PI) to the cells at6.a final concentration of 1 µg/mL. Keep the resuspended cells on ice.Filter the cells using suitable filters before analyzing them on a flow cytometer with single7.cell sorting capability.Sort PI-negative cells into a 96-well plate containing 100 μL of complete growth medium. If8.desired, you can use 1X antibiotics with the complete growth medium.Incubate the plates in a 37°C, 5% CO2 incubator.9.Scan the plates for single cell colonies as soon as small aggregates of cells are visible under10.a 4X microscope. Colonies should be large enough to see as soon as 7–14 days (usually afterfirst week, depending on the growth rate of the cell line). You can perform image analysis toensure that the colonies are derived from single cells.11.After image analysis, continue incubating the plates for an additional 2–3 weeks to expandthe clonal populations for further analysis and characterization.Characterize edited clones You can analyze the single cell clones for purity and the desired genotype (homozygous orheterozygous allele) by various molecular biology methods such as genotyping PCR, qPCR,next generation sequencing, or western blotting.Supporting tools At Thermo Fisher Scientific, you can find a wide variety of tools to meet your gene editingand validation needs, including Invitrogen™ LentiArray CRISPR and Silencer™ Select RNAilibraries for screening, primers for targeted amplicon sequencing, antibody collection forknock-out validation, and ORF collections and GeneArt™ gene synthesis service for cDNAexpression clones that can be used for rescue experiment reagents.thermofisher .com/support | thermofisher .com/askaquestion thermofisher .comLimited product warrantyLife Technologies Corporation and/or its affiliate(s) warrant their products as set forth in the Life Technologies’ General Terms and Conditions of Sale found on Life Technologies’ website at /us/en/home/global/terms-and-conditions.html . If you have any questions, please contact Life Technologies at www /support .Manufacturer: Thermo Fisher Scientific Baltics UAB | V. A. Graiciuno 8 | LT-02241 Vilnius, LithuaniaThe information in this guide is subject to change without notice.DISCLAIMER: TO THE EXTENT ALLOWED BY LAW, LIFE TECHNOLOGIES AND/OR ITS AFFILIATE(S) WILL NOT BE LIABLE FOR SPECIAL, INCIDENTAL, INDIRECT, PUNITIVE, MULTIPLE OR CONSEQUENTIAL DAMAGES IN CONNECTION WITH OR ARISING FROM THIS DOCUMENT, INCLUDING YOUR USE OF IT.Revision history:Pub. No. MAN0017066Important Licensing Information: These products may be covered by one or more Limited Use Label Licenses. By use of these products, you accept the terms and conditions of all applicable Limited Use Label Licenses.©2021 Thermo Fisher Scientific Inc. All rights reserved. All trademarks are the property of Thermo Fisher Scientific and its subsidiaries unless otherwise specified .。
Tagrisso(osimertinib)处方使用说明书2015年
英文版Tagrisso (osimertinib)药品使用说明书用于有特定表皮生长因子受体(EGFR)T790M突变及其它 EGFR 抑制剂耐药的晚期非小细胞肺癌患者HAOEYOU ( 好医友)HIGHLIGHTS OF PRESCRIBING INFORMATIONThese highlights do not include all the information needed to use TAGRISSO safely and effectively. See full prescribing information for TAGRISSO.TAGRISSO™ (osimertinib) tablet, for oral useInitial U.S. Approval: 2015--------------------------- INDICATIONS AND USAGE -------------------------- TAGRISSO is a kinase inhibitor indicated for the treatment of patients with metastatic epidermal growth factor receptor (EGFR) T790M mutation-positive non-small cell lung cancer (NSCLC), as detected by an FDA-approved test, who have progressed on or after EGFR TKI therapy. (1)This indication is approved under accelerated approval based on tumor response rate and duration of response. Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trials. (1)---------------------- DOSAGE AND ADMINISTRATION ---------------------- •Confirm the presence of T790M mutation in tumor specimens prior to initiation of treatment with TAGRISSO. (2.1)•80 mg orally once daily, with or without food. (2.2)--------------------- DOSAGE FORMS AND STRENGTHS -------------------- Tablets: 80 mg and 40 mg (3)------------------------------ CONTRAINDICATIONS ----------------------------- None. (4)----------------------- WARNINGS AND PRECAUTIONS ---------------------- •Interstitial Lung Disease (ILD)/Pneumonitis: Occurred in 3.3% of patients. Permanently discontinue TAGRISSO in patients diagnosedwith ILD/Pneumonitis. (5.1) •QTc Interval Prolongation: Monitor electrocardiograms and electrolytes in patients who have a history or predisposition for QTc prolongation, or those who are taking medications that are known to prolong the QTcinterval. Withhold then restart at a reduced dose or permanentlydiscontinue TAGRISSO. (2.4, 5.2)•Cardiomyopathy: Occurred in 1.4% of patients. Assess left ventricular ejection fraction (LVEF) before treatment and then every 3 monthsthereafter. (2.4, 5.3)•Embryo-Fetal Toxicity: TAGRISSO can cause fetal harm. Advise females of potential risk to the fetus and to use effective contraceptionduring treatment with TAGRISSO and for 6 weeks after final dose.Advise males to use effective contraception for 4 months, after the lastdose of TAGRISSO. (5.3, 8.1, 8.3)------------------------------ ADVERSE REACTIONS ----------------------------- Most common adverse reactions (≥25%) were diarrhea, rash, dry skin, and nail toxicity. (6.1)To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or or FDA at 1-800-FDA-1088 or /medwatch.------------------------------ DRUG INTERACTIONS ----------------------------- •Strong CYP3A Inhibitors: Avoid concurrent administration with TAGRISSO if possible. If no alternative exists, the patient should beclosely monitored for signs of toxicity. (7.1)•Strong CYP3A Inducers: Avoid if possible because concomitant use may decrease osimertinib plasma concentrations. (7.1)------------------------USE IN SPECIFIC POPULATIONS----------------------- Lactation: Do not breastfeed. (8.2)See 17 for PATIENT COUNSELING INFORMATION andFDA-approved patient labeling.Revised: 11/2015FULL PRESCRIBING INFORMATION: CONTENTS*1 INDICATIONS AND USAGE2 DOSAGE AND ADMINISTRATION2.1 Patient Selection2.2 Recommended Dosage Regimen2.3 Administration to Patients Who Have Difficulty Swallowing Solids2.4 Dose Modification for Adverse Reactions3 DOSAGE FORMS AND STRENGTHS4 CONTRAINDICATIONS5 WARNINGS AND PRECAUTIONS5.1 Interstitial Lung Disease/Pneumonitis5.2 QTc Interval Prolongation5.3 Cardiomyopathy5.4 Embryo-Fetal Toxicity6 ADVERSE REACTIONS6.1 Clinical Trials Experience7 DRUG INTERACTIONS7.1 Effect of Other Drugs on Osimertinib7.2 Effect of Osimertinib on Other Drugs8 USE IN SPECIFIC POPULATIONS8.1 Pregnancy8.2 Lactation8.3 Females and Males of Reproductive Potential8.4 Pediatric Use8.5 Geriatric Use8.6 Renal Impairment8.7 Hepatic Impairment11 DESCRIPTION12 CLINICAL PHARMACOLOGY12.1 Mechanism of Action12.2 Pharmacodynamics12.3 Pharmacokinetics13 NONCLINICAL TOXICOLOGY13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility14 CLINICAL STUDIES16 HOW SUPPLIED/STORAGE AND HANDLING17 PATIENT COUNSELING INFORMATION*Sections or subsections omitted from the full prescribing information are not listed.3182209 11/15FULL PRESCRIBING INFORMATION1 INDICATIONS AND USAGETAGRISSO is indicated for the treatment of patients with metastatic epidermal growth factor receptor (EGFR) T790M mutation-positive non-small cell lung cancer (NSCLC), as detected by an FDA-approved test, who have progressed on or after EGFR tyrosine kinase inhibitor (TKI) therapy.This indication is approved under accelerated approval based on tumor response rate and duration of response [see Clinical Studies (14)]. Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trials.2 DOSAGE AND ADMINISTRATION2.1 Patient SelectionConfirm the presence of a T790M EGFR mutation in tumor specimens prior to initiation of treatment with TAGRISSO [see Indications and Usage (1) and Clinical Studies (14)]. Information on FDA-approved tests for the detection of T790M mutations is available at/companiondiagnostics.2.2 Recommended Dosage RegimenThe recommended dose of TAGRISSO is 80 mg tablet once a day until disease progression or unacceptable toxicity. TAGRISSO can be taken with or without food.If a dose of TAGRISSO is missed, do not make up the missed dose and take the next dose as scheduled.2.3 Administration to Patients Who Have Difficulty Swallowing SolidsDisperse tablet in 4 tablespoons (approximately 50 mL) of non-carbonated water only. Stir until tablet is completely dispersed and swallow or administer through naso-gastric tube immediately. Do not crush, heat, or ultrasonicate during preparation. Rinse the container with 4 to 8 ounces of water and immediately drink or administer through the naso-gastric tube [see Clinical Pharmacology (12.3)].2.4 Dose Modification for Adverse ReactionsTable 1 Recommended Dose Modifications for TAGRISSO TargetOrgan Adverse Reaction a Dose ModificationPulmonary Interstitial lung disease(ILD)/PneumonitisPermanently discontinue TAGRISSO.Cardiac QTc† interval greater than 500msec on at least 2 separate ECGs bWithhold TAGRISSO until QTc interval is lessthan 481 msec or recovery to baseline if baselineQTc is greater than or equal to 481 msec, thenresume at 40 mg dose.QTc interval prolongation withsigns/symptoms of life threateningarrhythmiaPermanently discontinue TAGRISSO.Asymptomatic, absolute decreasein LVEF c of 10% from baselineand below 50%Withhold TAGRISSO for up to 4 weeks.• If improved to baseline LVEF, resume.• If not improved to baseline, permanentlydiscontinue.Symptomatic congestive heartfailurePermanently discontinue TAGRISSO.Other Grade 3 or higher adverse reaction Withhold TAGRISSO for up to 3 weeks. If improvement to Grade 0-2within 3 weeksResume at 80 mg or 40 mg daily.If no improvement within 3 weeks Permanently discontinue TAGRISSO.a Adverse reactions graded by the National Cancer Institute Common Terminology Criteria for Adverse Eventsversion 4.0 (NCI CTCAE v4.0).b ECGs = Electrocardiogramsc LVEF = Left Ventricular Ejection Fraction†QTc = QT interval corrected for heart rate3 DOSAGE FORMS AND STRENGTHS80 mg tablets: beige, oval and biconvex tablet marked with “AZ 80” on one side and plain on the reverse.40 mg tablets: beige, round and biconvex tablet marked with “AZ 40” on one side and plain on the reverse.4 CONTRAINDICATIONSNone.5 WARNINGS AND PRECAUTIONS5.1 Interstitial Lung Disease/PneumonitisAcross clinical trials, interstitial lung disease (ILD)/pneumonitis occurred in 3.3% (n=27) of TAGRISSO treated patients (n=813); 0.5% (n=4) were fatal.Withhold TAGRISSO and promptly investigate for ILD in any patient who presents with worsening of respiratory symptoms which may be indicative of ILD (e.g., dyspnea, cough and fever). Permanently discontinue TAGRISSO if ILD is confirmed [see Dosage and Administration (2.4) and Adverse Reactions (6)].5.2 QTc Interval ProlongationThe heart rate-corrected QT (QTc) interval prolongation occurs in patients treated with TAGRISSO. Of the 411 patients in Study 1 and Study 2, one patient (0.2%) was found to have a QTc greater than500 msec, and 11 patients (2.7%) had an increase from baseline QTc greater than 60 msec [see Clinical Pharmacology (12.2)].In Study 1 and 2, patients with baseline QTc of 470 msec or greater were excluded. Conduct periodic monitoring with ECGs and electrolytes in patients with congenital long QTc syndrome, congestive heart failure, electrolyte abnormalities, or those who are taking medications known to prolong the QTc interval. Permanently discontinue TAGRISSO in patients who develop QTc interval prolongation withsigns/symptoms of life threatening arrhythmia[see Dosage and Administration (2.4)].5.3 CardiomyopathyAcross clinical trials, cardiomyopathy (defined as cardiac failure, pulmonary edema, ejection fraction decreased or stress cardiomyopathy) occurred in 1.4% (n=11) of TAGRISSO treated patients (n=813); 0.2% (n=2) were fatal.In Study 1 and Study 2, Left Ventricular Ejection Fraction (LVEF) decline >10% and a drop to <50% occurred in 2.4% (9/375) of patients who had baseline and at least one follow up LVEF assessment. Assess LVEF by echocardiogram or multigated acquisition (MUGA) scan before initiation of TAGRISSO and then at 3 month intervals while on treatment. Withhold treatment with TAGRISSO if ejection fraction decreases by 10% from pretreatment values and is less than 50%. For symptomatic congestive heart failure or persistent, asymptomatic LV dysfunction that does not resolve within 4 weeks, permanently discontinue TAGRISSO [see Dosage and Administration (2.4)].5.4 Embryo-Fetal ToxicityBased on data from animal studies and its mechanism of action, TAGRISSO can cause fetal harm when administered to a pregnant woman. In animal reproduction studies, osimertinib caused post-implantation fetal loss when administered during early development at a dose exposure 1.5 times the exposure at therecommended human dose. When males were treated prior to mating with untreated females, there was an increase in preimplantation embryonic loss at plasma exposures of approximately 0.5-times those observed in patients at the 80 mg dose level.Advise pregnant women of the potential risk to a fetus.Advise females of reproductive potential to use effective contraception during treatment with TAGRISSO and for 6 weeks after the final dose. Advise males with female partners of reproductive potential to use effective contraception for 4 months after the final dose [see Use in Specific Populations (8.1), (8.3) and Clinical Pharmacology (12.3)].6 ADVERSE REACTIONSThe following adverse reactions are discussed in greater detail in other sections of the labeling: Interstitial Lung Disease/Pneumonitis [see Warnings and Precautions (5.1)]QTc Interval Prolongation [see Warnings and Precautions (5.2)]6.1 Clinical Trials ExperienceBecause clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.The data described below reflect exposure to TAGRISSO (80 mg daily) in 411 patients with EGFRT790M mutation-positive non-small cell lung cancer who received prior EGFR TKI therapy, in two single arm studies, Study 1 and Study 2. Patients with a past medical history of ILD or radiation pneumonitis that required steroid treatment, serious arrhythmia or baseline QTc interval greater than470 ms were excluded from Study 1 and Study 2. Baseline patient and disease characteristics were: median age 63 years, 13% of patients were ≥75 years old, female (68%), White (36%), Asian (60%), metastatic (96%), sites of brain metastases (39%), World Health Organization (WHO) performance status of 0 (37%) or 1 (63%), 1 prior line of therapy [EGFR-TKI treatment only, second line,chemotherapy-naïve (31%)], 2 or more prior lines of therapy (69%). Of the 411 patients, 333 patients were exposed to TAGRISSO for at least 6 months; 97 patients were exposed for at least 9 months; however no patient was exposed to TAGRISSO for 12 months.In Studies 1 and 2, the most common (>20%) adverse reactions (all grades) observed in TAGRISSO-treated patients were diarrhea (42%), rash (41%), dry skin (31%), and nail toxicity (25%). Dose reductions occurred in 4.4% of patients treated with TAGRISSO. The most frequent adverse reactions that led to dose reductions or interruptions were: electrocardiogram QTc prolonged (2.2%) and neutropenia (1.9%). Serious adverse reactions reported in 2% or more patients were pneumonia and pulmonary embolus. There were 4 patients (1%) treated with TAGRISSO who developed fatal adverse reactions of ILD/pneumonitis. Other fatal adverse reactions occurring in more than 1 patient included pneumonia (4 patients) and CVA/cerebral hemorrhage (2 patients). Discontinuation of therapy due to adverse reactions occurred in 5.6% of patients treated with TAGRISSO. The most frequent adverse reactions that led to discontinuation were ILD/pneumonitis and cerebrovascular accidents/infarctions.Tables 2 and 3 summarize the common adverse reactions and laboratory abnormalities observed in TAGRISSO-treated patients.Table 2 Adverse Reactions (>10% for all NCI CTCAE* Grades or >2% for Grades 3-4) in Study 1 and Study 2Adverse ReactionTAGRISSON=411All Grades Grade 3-4f % %Gastrointestinal disordersDiarrhea 42 1.0Nausea 17 0.5Decreased appetite 16 0.7Constipation 15 0.2Stomatitis 12 0 Skin disordersRash a41 0.5Dry skin b 31 0Nail toxicity c 25 0Pruritus 14 0 Eye Disorders d18 0.2 RespiratoryCough 14 0.2 GeneralFatigue 14 0.5 MusculoskeletalBack pain 13 0.7 Central Nervous SystemHeadache 10 0.2 InfectionsPneumonia 4 2.2 Vascular eventsVenous thromboembolism e7 2.4* NCI CTCAE v4.0.a Includes cases reported within the clustered terms for rash adverse events: Rash, rash generalized, rash erythematous, rash macular, rash maculo-papular, rash papular, rash pustular, erythema, folliculitis, acne, dermatitis and acneform dermatitis.b Includes dry skin, eczema, skin fissures, xerosis.c Includes nail disorders, nail bed disorders, nail bed inflammation, nail bed tenderness, nail discoloration, nail disorder, nail dystrophy, nail infection, nail ridging, onychoclasis, onycholysis, onychomadesis, paronychia.d Includes dry eye, vision blurred, keratitis, cataract, eye irritation, blepharitis, eye pain, lacrimation increased, vitreous floaters. Other ocular toxicities occurred in <1% of patients.e Includes deep vein thrombosis, jugular venous thrombosis, and pulmonary embolism.f No grade 4 events have been reported.Additional clinically significant adverse reactions occurring in 2% or more of patients treated with TAGRISSO included cerebrovascular accident (2.7%).Table 3 Common Laboratory Abnormalities (>20% for all NCI CTCAE Grades) in Study 1 and Study 2Laboratory AbnormalityTAGRISSON=411Change from BaselineAll Grades (%)Change from Baselineto Grade 3 or Grade 4(%)aClinical ChemistryHyponatremia 26 3.4Hypermagnesemia 20 0.7 HematologicLymphopenia 63 3.3Thrombocytopenia 54 1.2aAnemia 44 0.2Neutropenia 33 3.4a The only grade 4 laboratory abnormality was 1 patient with grade 4 thrombocytopenia.7 DRUG INTERACTIONSDrug interaction studies with inhibitors, inducers or substrates of CYP enzymes and transporters have not been conducted with TAGRISSO.7.1 Effect of Other Drugs on OsimertinibStrong CYP3A InhibitorsAvoid concomitant administration of TAGRISSO with strong CYP3A inhibitors, including macrolide antibiotics (e.g., telithromycin), antifungals (e.g., itraconazole), antivirals (e.g., ritonavir), nefazodone, as concomitant use of strong CYP3A inhibitors may increase osimertinib plasma concentrations. If no other alternative exists, monitor patients more closely for adverse reactions of TAGRISSO [see Dosage and Administrations (2.4) and Clinical Pharmacology (12.3)].Strong CYP3A InducersAvoid concomitant administration of TAGRISSO with strong CYP3A inducers (e.g., phenytoin, rifampicin, carbamazepine, St. John’s Wort) as strong CYP3A inducers may decrease osimertinib plasma concentrations [see Clinical Pharmacology (12.3)].7.2 Effect of Osimertinib on Other DrugsAvoid concomitant administration of TAGRISSO with drugs that are sensitive substrates of CYP3A, breast cancer resistance protein (BCRP), or CYP1A2 with narrow therapeutic indices, including but not limited to fentanyl, cyclosporine, quinidine, ergot alkaloids, phenytoin, carbamazepine, as osimertinib may increase or decrease plasma concentrations of these drugs [see Clinical Pharmacology (12.3)].8 USE IN SPECIFIC POPULATIONS8.1 PregnancyRisk SummaryBased on data from animal studies and its mechanism of action, TAGRISSO can cause fetal harm when administered to a pregnant woman. There are no available data on TAGRISSO use in pregnant women. Administration of osimertinib to pregnant rats was associated with embryolethality and reduced fetal growth at plasma exposures 1.5 times the exposure at the recommended human dose [see Data]. Advise pregnant women of the potential risk to a fetus.In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically-recognized pregnancies is 2% to 4% and 15% to 20%, respectively.DataAnimal DataWhen administered to pregnant rats prior to embryonic implantation through the end of organogenesis (gestation days 2-20) at a dose of 20 mg/kg/day, which produced plasma exposures of approximately 1.5 times the clinical exposure, osimertinib caused post-implantation loss and early embryonic death. When administered to pregnant rats from implantation through the closure of the hard palate (gestation days 6 to 16) at doses of 1 mg/kg/day and above (0.1-times the AUC observed in patients at the recommended dose of 80 mg), an equivocal increase in the rate of fetal malformations and variations was observed in treated litters relative to those of concurrent controls. When administered to pregnant dams at doses of30 mg/kg/day during organogenesis through lactation Day 6, osimertinib caused an increase in total litter loss and postnatal death. At a dose of 20 mg/kg/day, osimertinib administration during the same period resulted in increased postnatal death as well as a slight reduction in mean pup weight at birth that increased in magnitude between lactation days 4 and 6.8.2 LactationRisk SummaryThere are no data on the presence of osimertinib in human milk, the effects of osimertinib on the breastfed infant or on milk production. Administration to rats during gestation and early lactation was associated with adverse effects, including reduced growth rates and neonatal death [see Use in Specific Populations (8.1)]. Because of the potential for serious adverse reactions in breastfed infants from osimertinib, advise a lactating woman not to breastfeed during treatment with TAGRISSO and for 2 weeks after the final dose.8.3 Females and Males of Reproductive PotentialContraceptionFemalesAdvise females of reproductive potential to use effective contraception during treatment with TAGRISSO and for 6 weeks after the final dose [see Use in Specific Populations (8.1)].MalesAdvise male patients with female partners of reproductive potential to use effective contraception during and for 4 months following the final dose of TAGRISSO [see Nonclinical Toxicology (13.1)].InfertilityBased on animal studies, TAGRISSO may impair fertility in females and males of reproductive potential. It is not known if the effects on fertility are reversible [see Nonclinical Toxicology (13.1)].8.4 Pediatric UseThe safety and effectiveness of TAGRISSO in pediatric patients have not been established.8.5 Geriatric UseOne hundred eighty-seven (45%) of the 411 patients in clinical trials of TAGRISSO were 65 years of age and older, and 54 patients (13%) were 75 years of age and older. No overall differences in effectiveness were observed based on age. Exploratory analysis suggest a higher incidence of Grade 3 and 4 adverse reactions (32% versus 25%) and more frequent dose modifications for adverse reactions (23% versus 17%) in patients 65 years or older as compared to those younger than 65 years.8.6 Renal ImpairmentNo dedicated clinical studies have been conducted to evaluate the effect of renal impairment on the pharmacokinetics of osimertinib. Based on population pharmacokinetic analysis, no dose adjustment is recommended in patients with mild [creatinine clearance (CLcr) 60-89 mL/min] or moderate (CLcr 30-59 mL/min) renal impairment. There is no recommended dose of TAGRISSO for patients with severe renal impairment (CLcr <30 mL/min) or end-stage-renal disease [see Clinical Pharmacology (12.3)].8.7 Hepatic ImpairmentNo dedicated clinical studies have been conducted to evaluate the effect of hepatic impairment on the pharmacokinetics of osimertinib. Based on population pharmacokinetic (PK) analysis, no dose adjustment is recommended in patients with mild hepatic impairment [total bilirubin <upper limit of normal (ULN) and AST between 1 to 1.5 times ULN or total bilirubin between 1.0 to 1.5 times ULN and any AST]. There is no recommended dose for TAGRISSO for patients with moderate or severe hepatic impairment [see Clinical Pharmacology (12.3)].11 DESCRIPTIONOsimertinib is a kinase inhibitor for oral administration. The molecular formula for osimertinib mesylate is C28H33N7O2•CH4O3S, and the molecular weight is 596 g/mol. The chemical name is N-(2-{2-dimethylaminoethyl-methylamino}-4-methoxy-5-{[4-(1-methylindol-3-yl)pyrimidin-2-yl]amino}phenyl)prop-2-enamide mesylate salt. Osimertinib has the following structural formula (as osimertinib mesylate):TAGRISSO tablets contain 40 or 80 mg of osimertinib, equivalent to 47.7 and 95.4 mg of osimertinib mesylate, respectively. Inactive ingredients in the tablet core are mannitol, microcrystalline cellulose, low-substituted hydroxpropyl cellulose and sodium stearyl fumarate. The tablet coating consists of polyvinyl alcohol, titanium dioxide, macrogol 3350, talc, ferric oxide yellow, ferric oxide red and ferric oxide black.12 CLINICAL PHARMACOLOGY12.1 Mechanism of ActionOsimertinib is kinase inhibitor of the epidermal growth factor receptor (EGFR), which binds irreversibly to certain mutant forms of EGFR (T790M, L858R, and exon 19 deletion) at approximately 9-fold lower concentrations than wild-type. In cultured cells and animal tumor implantation models, osimertinib exhibited anti-tumor activity against NSCLC lines harboring EGFR-mutations (T790M/L858R, L858R, T790M/exon 19 deletion, and exon 19 deletion) and, to a lesser extent, wild-type EGFR amplifications. Two pharmacologically-active metabolites (AZ7550 and AZ5104 circulating at approximately 10% of the parent) with similar inhibitory profiles to osimertinib have been identified in the plasma after oral administration of osimertinib. AZ7550 showed a similar potency to osimertinib, while AZ5104 showed greater potency against exon 19 deletion and T790M mutants (approximately 8-fold) and wild-type (approximately 15-fold) EGFR. In vitro, osimertinib also inhibited the activity of HER2, HER3, HER4, ACK1, and BLK at clinically relevant concentrations.12.2 PharmacodynamicsCardiac ElectrophysiologyThe QTc interval prolongation potential of osimertinib was assessed in 210 patients who received TAGRISSO 80 mg daily in Study 2. A central tendency analysis of the QTcF data at steady-state demonstrated that the maximum mean change from baseline was 16.2 (upper bound of two-sided 90% confidence interval (CI) 17.6) msec. A pharmacokinetic/pharmacodynamic analysis in Study 2 suggesteda concentration-dependent QTc interval prolongation of 14 msec (upper bound of two-sided 90% CI:16 msec) at a dose of osimertinib 80 mg.12.3 PharmacokineticsThe area under the plasma concentration-time curve (AUC) and maximal plasma concentration (C max) of osimertinib increased dose proportionally over 20 to 240 mg dose range (i.e., 0.25 to 3 times the recommended dosage) after oral administration and exhibited linear pharmacokinetics (PK). Administration of TAGRISSO orally once daily resulted in approximately 3-fold accumulation withsteady state exposures achieved after 15 days of dosing. At steady state, the C max to C min (minimal concentration) ratio was 1.6-fold.AbsorptionThe median time to C max of osimertinib was 6 hours (range 3-24 hours).Following administration of a 20 mg TAGRISSO tablets with a high-fat, high-calorie meal (containing approximately 58 grams of fat and 1000 calories), the C max and AUC of osimertinib increased by 14% and 19% respectively, compared to fasting conditions.DistributionThe mean volume of distribution at steady-state (V ss/F) of osimertinib was 986 L. Plasma protein binding of osimertinib is likely high based on its physiochemical properties.EliminationOsimertinib plasma concentrations decreased with time and a population estimated mean half-life of osimertinib was 48 hours, and oral clearance (CL/F) was 14.2 (L/h).MetabolismThe main metabolic pathways of osimertinib were oxidation (predominantly CYP3A) and dealkylation in vitro. Two pharmacologically active metabolites (AZ7550 and AZ5104) have been identified in the plasma after TAGRISSO oral administration. The geometric mean exposure (AUC) of each metabolite (AZ5104 and AZ7550) was approximately 10% of the exposure of osimertinib at steady-state. ExcretionOsimertinib is primarily eliminated in the feces (68%) and to a lesser extent in the urine (14%). Unchanged osimertinib accounted for approximately 2% of the elimination.Specific PopulationsNo clinically significant differences in the pharmacokinetics of osimertinib were observed based on age, sex, ethnicity, body weight, smoking status, mild (CLcr 60-89 mL/min) or moderate (CLcr 30-59mL/min) renal impairment, or mild hepatic impairment (total bilirubin <ULN and AST between 1 to 1.5x ULN or total bilirubin between 1.0 to 1.5 times ULN and any AST ). There are no data on the pharmacokinetics of osimertinib in patients with severe renal impairment (CLcr less than 30 mL/min) or with moderate to severe hepatic impairment (moderate: total bilirubin between 1.5 to 3.0 times ULN and any AST, and severe: total bilirubin between 3.0-10 times ULN and any AST).Drug InteractionsEffect of Other Drugs on TAGRISSO:Strong CYP3A Inhibitors: Clinical studies evaluating TAGRISSO in the presence of strong CYP3A inhibitors have not been conducted [see Drug Interactions (7.1)].Strong CYP3A Inducers: Clinical studies evaluating TAGRISSO in the presence of strong CYP3A inducers have not been conducted [see Drug Interactions (7.1)].Gastric Acid Reducing Agents: The exposure of osimertinib was not affected by concurrent administration of a single 80 mg TAGRISSO tablet following 40 mg omeprazole administration for 5 days.Effect of Osimertinib on Other Drugs:CYP450 Metabolic Pathways: Osimertinib is a competitive inhibitor of CYP3A, but not CYP2C8, 1A2, 2A6, 2B6, 2C9, 2C19, 2D6 and 2E1 in vitro. Osimertinib induced CYP3A4 (Pregnane X dependent) and CYP1A2 enzymes.Transporter Systems: Based on in vitro studies, osimertinib is a substrate of P-glycoprotein and BCRP and is not a substrate of OATP1B1 and OATP1B3. Osimertinib is an inhibitor of BCRP and does not inhibit P-glycoprotein, OAT1, OAT3, OATP1B1, OATP1B3, MATE1, MATE2K and OCT2 in vitro.13 NONCLINICAL TOXICOLOGY13.1 Carcinogenesis, Mutagenesis, Impairment of FertilityCarcinogenicity studies have not been performed with osimertinib. Osimertinib did not cause genetic damage in in vitro and in vivo assays.Based on studies in animals, male fertility may be impaired by treatment with TAGRISSO. Degenerative changes were present in the testes in rats and dogs exposed to osimertinib for 1 month or more with evidence of reversibility in the rat. Following administration of osimertinib to rats for approximately 10 weeks at a dose of 40 mg/kg, at exposures 0.5-times the AUC observed in patients at the recommended dose of 80 mg, there was a reduction in male fertility, demonstrated by increased pre-implantation loss in untreated females mated to treated males.Nonclinical female fertility studies have not been conducted. In repeat dose toxicity studies, histological evidence of anestrus, corpora lutea degeneration in the ovaries and epithelial thinning in the uterus and vagina were seen in rats exposed to osimertinib for 1 month or more at exposures 0.3-times the AUC observed in patients at the recommended dose of 80 mg. Findings in the ovaries seen following 1 month of dosing exhibited evidence of reversibility.14 CLINICAL STUDIESThe efficacy of TAGRISSO was demonstrated in two multicenter, single-arm, open-label clinical trials, Study 1 and Study 2, in patients with metastatic EGFR T790M mutation-positive NSCLC who had progressed on prior systemic therapy, including an EGFR TKI. All patients were required to have EGFR T790M mutation-positive NSCLC as detected by the cobas® EGFR mutation test and received TAGRISSO 80 mg once daily. The major efficacy outcome measure of both trials was objective response rate (ORR) according to RECIST v1.1 as evaluated by a Blinded Independent Central Review (BICR). Duration of response (DOR) was an additional outcome measure.。